
Contents
- Name of bone
- Location/Articulation
- Muscle and ligament attachments
- Surface anatomy
- Radiography
- Physical examination
- Embryology
- Anomalies
- Injuries/Disorders
Name of bone
Parietal
Location/Articulation
The union of the parietal bones forms the sides and roof of the cranium. Each bone is irregularly quadrilateral in form, and has two surfaces, four borders, and four angles.
Muscle and ligament attachments
Surface anatomy
External
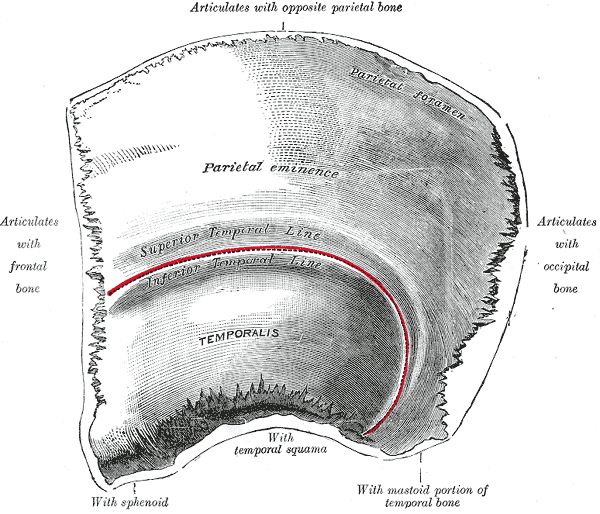
- The external surface of the parietal bone is convex, smooth, and marked near the center by the parietal eminence (tuber parietale), which indicates the point where ossification began.
- Crossing the middle of the bone in an arched direction are two curved lines, the superior and inferior temporal lines. The former gives attachment to the temporal fascia, and the latter indicates the upper limit of the muscular origin of the temporalis.
- Above these lines the bone is covered by the galea aponeurotica (epicranial aponeurosis). Below the lines, the bone forms part of the temporal fossa and affords attachment to the temporalis muscle.
- At the back part and close to the upper, or sagittal, border is the parietal foramen, which transmits a vein to the superior sagittal sinus, and sometimes a small branch of the occipital artery. The parietal foramen is not always present, and when it is, its size can vary considerably.
Internal
- The internal surface is concave. It presents depressions corresponding to the cerebral convolutions and numerous furrows (grooves) for the ramifications of the middle meningeal artery. The latter run upward and backward from the sphenoidal angle, and from the central and posterior part of the squamous border.
- Along the upper margin is a shallow groove, which, together with that on the opposite parietal, forms a channel – the sagittal sulcus – for the superior sagittal sinus. The edges of the sulcus afford attachment to the falx cerebri.
- Near the groove are several depressions, best marked in the skulls of older persons, for the arachnoid granulations (Pacchionian bodies).
- In the groove is the internal opening of the parietal foramen, when that aperture exists.
Borders
- The sagittal border, the longest and thickest, is dentated (has toothlike projections) and articulates with its fellow of the opposite side, forming the sagittal suture.
- The squamous border is divided into three parts:
- The anterior is thin and pointed, bevelled at the expense of the outer surface, and overlapped by the tip of the great wing of the sphenoid.
- The middle portion is arched, bevelled at the expense of the outer surface, and overlapped by the squama of the temporal.
- The posterior part is thick and serrated for articulation with the mastoid portion of the temporal.
- The frontal border is deeply serrated and bevelled at the expense of the outer surface above and of the inner below. It articulates with the frontal bone, forming half of the coronal suture. The point where the coronal suture intersects with the sagittal suture forms a T-shape and is called the bregma.
- The occipital border, deeply denticulated (finely toothed), articulates with the occipital bone, forming half of the lambdoid suture. That point where the sagittal suture intersects the lambdoid suture is called the lambda, because of its resemblance to the Greek letter.
Angles
- The frontal angle, practically a right angle, corresponds with the point of meeting of the sagittal and coronal sutures, called the bregma. In the fetal skull and for about a year and a half after birth, this region is membranous and is called the anterior fontanelle.
- The sphenoidal angle, thin and acute, is received into the interval between the frontal bone and the great wing of the sphenoid. Its inner surface is marked by a deep groove, sometimes a canal, for the anterior divisions of the middle meningeal artery.
- The occipital angle is rounded and corresponds with the point of meeting of the sagittal and lambdoidal sutures, called the lambda. In the fetus this part of the skull is membranous and is called the posterior fontanelle.
- The mastoid angle is truncated. It articulates with the occipital bone and with the mastoid portion of the temporal, and presents on its inner surface a broad, shallow groove that lodges part of the transverse sinus. The point of meeting of this angle with the occipital and the mastoid part of the temporal is called the asterion.

Figure 1. Surface anatomy of the parietal bone
Radiography
Physical examination
Embryology
The parietal bone is ossified in membrane from a single center, which appears at the parietal eminence about the 8th week of fetal life. Ossification gradually extends in a radial manner from the center toward the margins of the bone. The angles are consequently the last parts formed, and it is here that the fontanelles exist.
Occasionally the parietal bone is divided into two parts, upper and lower, by an antero-posterior suture. This variation is known as os inca, or an “Inca bone,” because anthropologists first discovered it among Incan remains in South America.
Anomalies
Injuries/Disorders
Attachments:

Last Updated on June 27, 2024
🔗 Knowledge Graph & Clinical Correlates
OrthopaedicsOne Living Semantic Network🩺 Clinical Conditions & Indications
- Wigns There are three categories of diagnostic data collected during the physical examination (sign, symptom, and that in between)...
- Why have a privacy policy for my office Original Clinical Contribution: Authored for the OrthopaedicsOne General Orthopaedics Specialty Section. Preserved, digitized, and updated to modern evidence-based...
- Why have a practice website Original Clinical Contribution: Authored for the OrthopaedicsOne General Orthopaedics Specialty Section. Preserved, digitized, and updated to modern evidence-based...
- Who should undergo biopsy of a bone lesion Patient selection for a biopsy is important: It is intended to confirm the radiologic diagnosis in patients with...
🔬 Anatomy, Pathology & Diagnostics
- Wrist joint Wrist and Carpus
💼 Practice Management & Professional Operations
- Winthrop M. Phelps History of Orthopaedics
- Willis Cohoon Campbell History of Orthopaedics
- William Waugh History of Orthopaedics
- William Ward Plummer History of Orthopaedics
- William Thomas Gordon Pugh History of Orthopaedics
- William Stewart Halsted History of Orthopaedics
- William Stevenson Baer History of Orthopaedics
- William Morant Baker History of Orthopaedics